01
Makeup Tips
Eyeshadow placement, blending techniques, and common mistakes to avoid for a more open, lifted look.
Explore →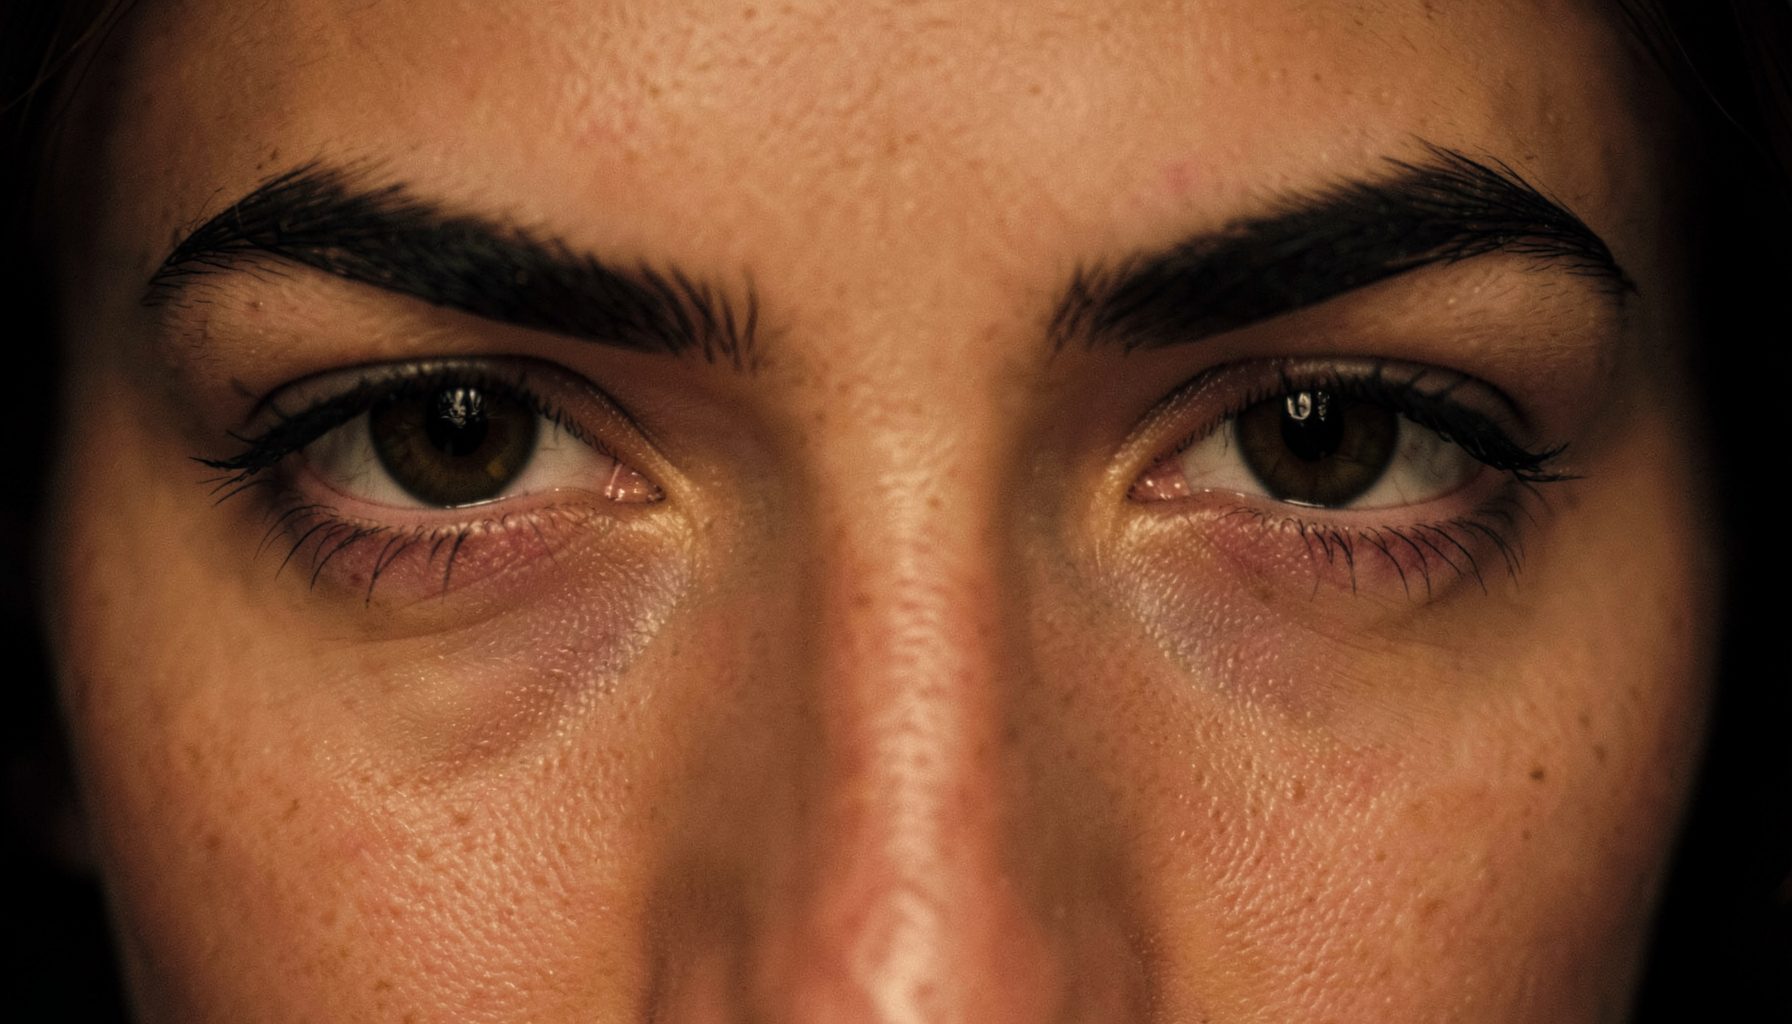
Eye Shape Guide
Understand your eye shape, master makeup techniques, and explore every treatment option — from Botox brow lifts to surgical solutions.
Explore the Site
Eyeshadow placement, blending techniques, and common mistakes to avoid for a more open, lifted look.
Explore →Winged liner, smudge prevention, and techniques that work with hooded lids to make eyes appear larger.
Explore →Non-surgical Botox brow lifts and surgical options including blepharoplasty, explained clearly.
Explore →Five false lash styles suited to hooded eyes, plus curler and mascara guidance for maximum lift.
Explore →
What Are Hooded Eyes?
Hooded eyes are a natural eye shape where an excess piece of skin from the brow bone partially or completely covers the eyelid. The result can make eyes appear smaller or more tired than they feel.
This shape can be present from birth due to genetics, or it can develop over time. Known causes include aging, genetic traits, eye rubbing, body fatness, muscle structure, trauma, solar radiation, and sleep apnea.
Having one hooded eye and one more open-looking eye is more common than many people realise. “Hooded” usually describes a visible upper-eyelid crease partly covered by a fold of skin; a monolid has little or no visible crease, while deep-set eyes sit more deeply within the eye socket. These labels describe appearance rather than a diagnosis, and small differences between the sides can be entirely normal.
The explanation can involve anatomy, ageing, eyesight or, less commonly, a medical condition. Anisometropia means that the two eyes have different refractive errors, but it does not directly produce a hooded upper eyelid. Understanding which factor is responsible helps you choose effective makeup, obtain the right eye examination or consider treatment without expecting perfectly identical eyes.
The upper eyelid is a moving structure. Its crease forms as the levator muscle lifts the lid and the skin folds, while orbital fat sits behind it. The brow, connective tissue and muscles around the eye also influence how much lid shows. If one levator tendon is slightly weaker, one brow sits lower or the fat and skin are distributed differently, that side can appear more hooded even when the other eye looks open and defined. A hooded eye identification guide can help distinguish these visible features from monolids.
Congenital asymmetry often shows up during the teenage years and remains stable. With age, the levator tendon can become less efficient, excess skin can gather above the lash line and the brow may descend, making one fold more pronounced. Australia’s high UV exposure adds a skin-quality variable: years of sun can reduce elasticity and make laxity easier to see. Swelling from allergy, fluid retention or uneven fat prolapse can also change the balance temporarily.
Perception matters as well. Facial asymmetry, camera angle, brow grooming and the shadow cast by the lid can exaggerate the difference. Australian actor Margot Robbie is frequently cited in beauty coverage for a pronounced upper-lid fold, while Bella Hadid is often discussed for deep-set eyes; such examples are illustrative rather than medical assessments. If only photographs suggest a change, compare current images with older ones taken in similar light and position.
Anisometropia is usually a difference in focusing power: one eye may be short-sighted while the other is long-sighted, or their astigmatism may differ. The brain may favour clearer vision from one eye, and blurred vision can encourage habitual squinting, closing one eye or raising one brow. Those habits can make one lid look more compressed, yet they do not change the eyelid’s basic structure. A new prescription, poorly fitted glasses or contact lenses can also make previously hidden asymmetry more noticeable.
Anisometropia is not the same as amblyopia, commonly called lazy eye, and it is separate from strabismus, where the eyes point in different directions. In children, a large uncorrected difference can interfere with visual development, so early testing is important. Adults with long-standing unequal prescriptions may have visual fatigue, headaches or difficulty with depth perception. An optometrist or ophthalmologist can measure each eye, compare the refractive prescriptions, check eye dominance and assess how the brain uses the two images.
A persistent one-sided droop needs assessment because it may be more than an eyelid-fold variation. Causes can include age-related ptosis, trauma, thyroid eye disease, myasthenia gravis or cranial-nerve problems. Seek urgent medical care for a sudden lid drop accompanied by double vision, unequal pupils, severe headache, weakness or nausea; in Australia, call 000 for a medical emergency. If one eye is covered by the drooping lid, is drifting outward or has reduced vision, arrange prompt review rather than treating the appearance with cosmetics alone.
Makeup for unequal hooding should balance the visible opening rather than force both folds into the same shape. Start by identifying the mobile lid on each side, because a heavy shadow placed over skin that already covers the crease can make the eye look smaller. Professionals often use thin layers, controlled liner and strategic highlighting. A review of backstage eye makeup products shows how backstage choices prioritise eye shape, longevity and quick transformation.
Concealer can create a soft, even base, but keep it sheer over the fold and avoid a hard pale stripe directly beneath it. A translucent cut-crease shade placed just above the visible fold can make it look higher without drawing a false line too far from the lash line. Brows are especially useful: lift the weaker brow slightly, fill sparse areas and keep the tails balanced. On the more open eye, keep the crease cleaner and the wing restrained so it does not compete with the hooded side.
Eyeliner and lashes can compensate for lost lid space. A thin waterline or softly darkened upper lash line often reads more clearly than a thick band that disappears under the fold, while a small upward wing can define the outer corner. Curl the lashes and use a lengthening, waterproof mascara; a lash lift may help if the technician can safely lift the natural lashes without pulling the lid down. Australian shoppers can compare TIRTIL, Clinique, Maybelline and L’Oréal options at Priceline, Sephora, JB Hi-Fi and Chemist Warehouse, with prices generally shown in Australian dollars and GST included.
A Botox brow lift may help when a low brow contributes to the hooded appearance. Injecting selected muscles around the brow can reduce downward pull and create slightly more visible lid space, but it cannot remove excess skin or alter a structurally deep crease. Temporary swelling can hide the result initially. Common risks include bruising, headache, brow asymmetry, eyelid droop and double vision, particularly if the product is placed too close to the eyelid. In Australia, ask whether the injector is appropriately registered with AHPRA and whether the proposed use is approved or off-label for the product.
Upper blepharoplasty is a surgical option for excess upper-lid skin or a deep hooded fold. The procedure may reshape the crease, reposition tissue and improve the visible opening, so it suits people seeking a permanent structural change. Before surgery, the clinician should review your medical history, medicines, allergies, goals and previous eye procedures; do not stop prescribed blood thinners without medical advice. Aftercare typically includes careful wound care, swelling management, sunglasses and strong sun protection. Risks include infection, scarring, asymmetry, persistent swelling, dry eye, corneal exposure, incomplete correction and revision.
Cosmetic procedures are widely offered in Sydney, Melbourne, Brisbane and other Australian cities, but standards and prices vary. A plastic surgeon who holds FRACS, a cosmetic physician and an optometrist or ophthalmologist may all be relevant, although their roles differ. Ask who performs the procedure, where it is performed, what follow-up is included and how complications are handled. Fees should be quoted in AUD, usually with GST included. Neither Botox nor blepharoplasty corrects anisometropia, so glasses, contact lenses or refractive advice remain separate from any eyelid treatment.
| Finding | Appearance or symptom | Main point | Sensible next step |
|---|---|---|---|
| Open-looking upper lid | A defined crease and clearly visible mobile lid | A normal appearance with no structural concern | Makeup can enhance the crease and lash line |
| True hooded lid | Part of the crease is covered by a fold of skin | May involve skin, fat, brow position or levator strength | Compare the sides and assess whether the appearance is changing |
| Unilateral asymmetry | One eye appears smaller, lower or differently folded | Can be developmental, age-related or a sign of ptosis | Seek an eye examination if it is new, worsening or affects vision |
| Anisometropia | Unequal blur, squinting or visual discomfort may occur | A refractive difference does not directly create hooding | Have each eye measured and discuss suitable vision correction |
| Ptosis or strabismus | Drooping, an uneven pupil or visual disturbance needs attention | These can indicate conditions beyond ordinary eyelid variation | Seek prompt medical review, particularly with sudden symptoms |
A short personal record can reveal whether the difference is structural, temporary or changing. Keep notes that separate what you see in a mirror from what an optometrist can measure, and use those notes to guide both cosmetic choices and medical review.
Look for patterns and warning signs
Prepare before professional review
If the asymmetry is new, worsening or affects vision, book a comprehensive eye assessment with an optometrist or ophthalmologist and bring your records. If it is long-standing and cosmetic, arrange a tailored makeup session or a consultation with a qualified clinician, then proceed with the option that matches your anatomy and priorities.
Surgical Option
For those seeking a more lasting result, plastic surgery — including blepharoplasty — is covered as a treatment option for hooded eyes. Surgery addresses the excess skin directly and is considered an alternative to non-surgical approaches like Botox.
The site's surgery guide explains the procedure, what to expect, and how it compares to non-surgical routes, helping readers make informed decisions about their options.
Read the Surgery Guide →Famous Faces
Hooded eyes can enhance facial expressions and contribute to a distinctive, memorable look. These ten well-known figures all share the eye shape.
Jennifer Aniston
Leonardo DiCaprio
Solange Knowles
Taylor Swift
Michelle Williams
Robert Pattinson
Blake Lively
Selena Gomez
Gigi Hadid
Benicio del Toro
Side by Side
False Lash Guide
Varied length spikes create texture and the illusion of depth without weighing down the lid.
Longer outer-corner lashes draw the eye outward and upward, counteracting the hood effect.
A uniform, moderate length that adds definition without overwhelming a hooded lid.
Applied only to the outer half, these open up the eye shape and are easier to manage on hooded lids.
A strong upward curl (D or L curl) lifts lashes away from the hood, keeping them visible throughout the day.
The guide also covers lash curlers, mascara recommendations, and step-by-step instructions for fixing false lashes on hooded eyelids.
Full Lash Guide →Get in Touch
Whether you are just beginning your makeup journey or have been experimenting with different looks for years, we are glad you are here.
General Feedback
Share your thoughts on the site or suggest topics you'd like covered.
Looking for a Specific Tip?
Ask about a particular technique or eye-shape challenge.
Product Questions
Questions about products mentioned across the site.
Human Resources or Business Inquiries
Partnership, collaboration, or business-related correspondence.