01
Makeup Tips
Eyeshadow placement, blending techniques, and common mistakes to avoid for a more open, lifted look.
Explore →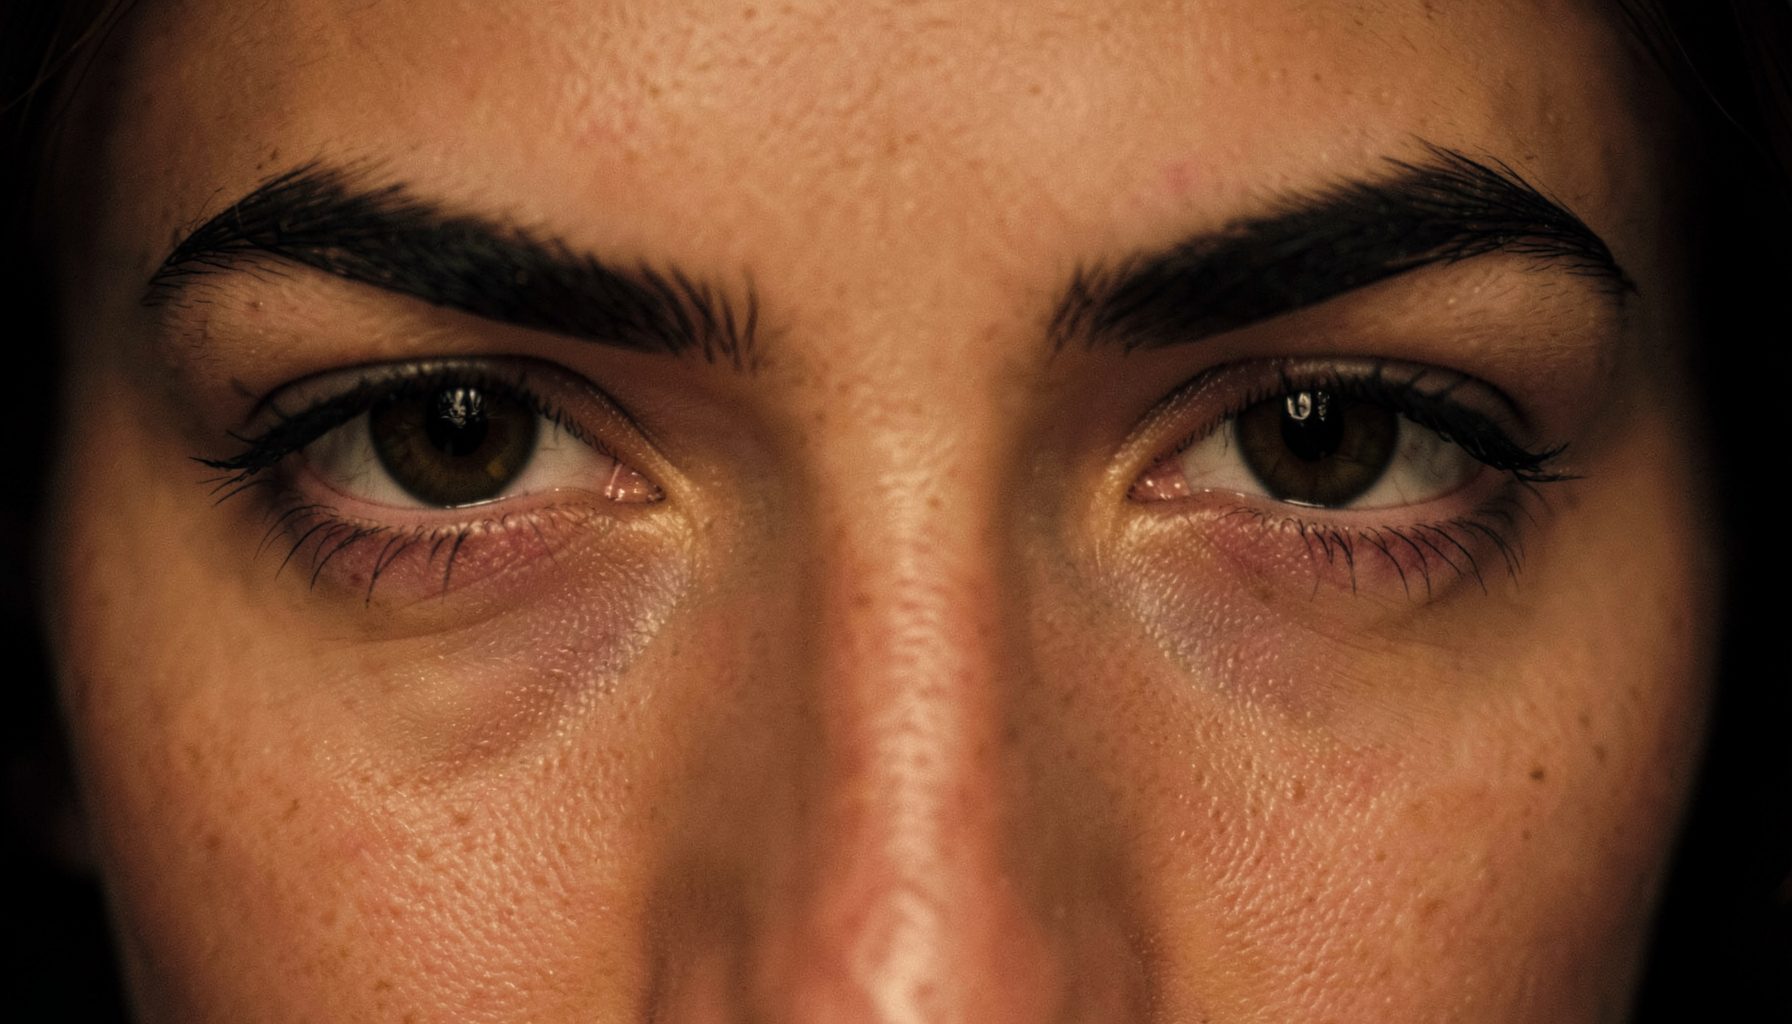
Eye Shape Guide
Understand your eye shape, master makeup techniques, and explore every treatment option — from Botox brow lifts to surgical solutions.
Explore the Site
Eyeshadow placement, blending techniques, and common mistakes to avoid for a more open, lifted look.
Explore →Winged liner, smudge prevention, and techniques that work with hooded lids to make eyes appear larger.
Explore →Non-surgical Botox brow lifts and surgical options including blepharoplasty, explained clearly.
Explore →Five false lash styles suited to hooded eyes, plus curler and mascara guidance for maximum lift.
Explore →
What Are Hooded Eyes?
Hooded eyes are a natural eye shape where an excess piece of skin from the brow bone partially or completely covers the eyelid. The result can make eyes appear smaller or more tired than they feel.
This shape can be present from birth due to genetics, or it can develop over time. Known causes include aging, genetic traits, eye rubbing, body fatness, muscle structure, trauma, solar radiation, and sleep apnea.
Hooded eyes occur when the upper eyelid crease is partly hidden by a fold of skin. The effect can make the eye opening look smaller and create shadowing that resembles tiredness. Some people also have one eye sitting lower than the other, so the result needs to reflect natural facial balance rather than a single ideal crease. Learn more about Thehoodedeyes.com.
Elective blepharoplasty can remove or reposition tissue around the eyelids, but every operation carries uncertainty. Infection, dry eye and asymmetry are important blepharoplasty risks, and their likelihood varies with anatomy, health and technique. A realistic consultation should explain what can be controlled, what cannot and which changes might require further treatment.
Understanding what hooded eyes mean helps distinguish a cosmetic contour concern from a medical eyelid problem. Hooding can result from ageing, genetics, a descending brow, excess skin or natural differences in eyebrow and eyelid position. It does not automatically mean the eyelid-raising muscle is weak.
Upper blepharoplasty usually involves removing excess upper eyelid skin and sometimes fat. Lower blepharoplasty addresses bags, hollows or lax skin beneath the eye. A brow lift changes the position of the brow rather than removing eyelid skin, while ptosis surgery addresses a drooping eyelid margin. Confusing these procedures can lead to an unsatisfactory outcome because they treat different anatomical problems.
Risk depends on the proposed technique and the condition being corrected. A straightforward upper-lid removal differs considerably from complex fat repositioning, lower-lid surgery or correction of previous eyelid procedures. If a patient has facial nerve weakness, incomplete eyelid closure or a history of corneal damage, the surgeon may recommend a different approach or advise against surgery.
Wound infection can occur after eyelid surgery, although careful technique and follow-up reduce the likelihood. Increasing pain, swelling, redness, warmth or discharge after the first few days should be reported promptly, particularly if fever develops. Most superficial infections respond to prescribed treatment, but an infection that spreads deeper around the eye is serious and requires urgent hospital assessment.
Bleeding during or after surgery can produce a haematoma and make one eyelid appear temporarily swollen or uneven. Rarely, bleeding behind the eye can threaten vision. Scarring is another possibility, with the final appearance depending on skin quality, healing and incision placement. Anaesthesia-related problems, including nausea, allergic reactions or cardiac complications, can also occur even though serious events are uncommon.
Smoking, poorly controlled diabetes, some autoimmune conditions and medications that affect bleeding or healing can increase complications. Patients should disclose all medicines, supplements, allergies, prior eye operations and contact-lens use. Blood thinners should not be stopped without advice from the prescribing clinician, because the medical reason for taking them must be considered alongside surgical bleeding risk.
Dry eye is one of the most important risks to discuss because the eyelids normally spread tears evenly across the cornea. If too much skin is removed, or the eyelid is positioned too high, the eye may not close fully. This creates corneal exposure even when the operation looked technically successful. Tear production may remain normal while the tears evaporate more quickly because the lid no longer covers the eye properly.
Symptoms include grittiness, burning, fluctuating blurred vision, redness, light sensitivity and the feeling that something is in the eye. These effects can appear immediately or emerge as swelling settles. Temporary irritation is common, while persistent incomplete closure or severe surface damage can cause longer-lasting dry eye, scarring and, rarely, a change in vision. Lower eyelid surgery can also pull the lid away from the eye and worsen exposure.
Pre-operative assessment should identify existing dry eye, glaucoma, corneal problems and incomplete closure. An ophthalmologist or oculoplastic surgeon may be appropriate when ocular-surface disease is present. Prescribed lubricating drops, ointment and careful eyelid care can help, but they do not correct an eyelid that remains badly positioned. Persistent symptoms deserve an eye assessment rather than repeated use of over-the-counter drops alone.
Asymmetry may already be present before surgery because the eyebrows, eyelid creases, fat distribution or eyelid muscles differ between sides. Swelling can temporarily exaggerate it, but uneven fat removal, an unequal crease or inconsistent healing can make the difference permanent. A surgeon should explain which asymmetry is structural and which may improve, rather than promising exact symmetry.
Over-correction can leave an eye looking hollow, high or excessively open. Under-correction may preserve hooding that the patient hoped to remove. Lower-lid surgery carries particular risks of ectropion, where the eyelid turns outward, and scleral show, where more of the white of the eye becomes visible. A drooping eyelid margin, double vision or noticeable contour changes may also occur.
Small differences can sometimes be adjusted with a revision, but revision surgery has its own recovery and risks. Scars usually fade over time, yet their final appearance cannot be guaranteed, and revision may be delayed until swelling and skin settling are complete. Patients should discuss where scars will sit, how long final results may take and whether additional surgery could be required.
Clinics around Bondi Junction in Sydney, South Melbourne and Brisbane’s central business district offer eyelid procedures, but location is less important than credentials. Check the surgeon’s registration through AHPRA and confirm training in plastic or oculoplastic surgery. Fellowship of the Royal Australasian College of Surgeons, recognised plastic surgery society membership and experience with the specific eyelid procedure all provide useful evidence of expertise.
For surgery sought mainly to change a hooded appearance, Medicare generally provides no rebate, and most private health policies treat blepharoplasty as cosmetic or excluded. Rare functional claims require assessment by the insurer. Australian clinics may market the operation as an eyelid refresh or cosmetic lid tweak, but those phrases do not describe the technique. Compare itemised quotes in Australian dollars and ask what includes the surgeon, facility, anaesthesia, follow-up, medication and any revision costs.
Before surgery, complete the prescribed medical checks, stop smoking if applicable and follow instructions about makeup, contact lenses and medications. Arrange transport home, assistance for the first day and time away from work. Photographs may be taken for comparison, but they do not guarantee an exact result. The surgeon should explain whether the procedure is being performed under local anaesthesia with sedation or under general anaesthesia.
Afterward, use prescribed medication, rest with the head supported and avoid rubbing the eyes. Cold compresses can ease swelling if the surgeon approves them, while direct ice should not be placed on the skin. Many patients avoid swimming because of chlorine and infection risk, and use sunglasses and broad-brimmed hats for UV protection. Makeup and contact lenses should be resumed only at the stated stage, often after the wounds have closed and the surgeon agrees.
Sudden blurred vision, severe eye pain, bleeding that does not stop, a rapidly protruding eye, inability to close the eyelid, worsening redness, fever or a marked new difference between the eyes require urgent contact with the surgeon or emergency assessment. Patients with persistent grittiness, watering or light sensitivity should also seek review rather than assuming the symptom is part of normal healing.
Surgical brow lift, blepharoplasty and Botox address hooding differently. Botox can temporarily relax muscles that pull the brow down, but it cannot remove excess skin, usually lasts only a few months and can cause bruising, eyelid droop or temporary double vision. A detailed Botox versus surgery comparison can help establish which approach fits the anatomy and desired result. Book a consultation with a suitably qualified Australian surgeon, bring your medication list and leave with a clear plan for risks, aftercare and the management of complications.
Surgical Option
For those seeking a more lasting result, plastic surgery — including blepharoplasty — is covered as a treatment option for hooded eyes. Surgery addresses the excess skin directly and is considered an alternative to non-surgical approaches like Botox.
The site's surgery guide explains the procedure, what to expect, and how it compares to non-surgical routes, helping readers make informed decisions about their options.
Read the Surgery Guide →Famous Faces
Hooded eyes can enhance facial expressions and contribute to a distinctive, memorable look. These ten well-known figures all share the eye shape.
Jennifer Aniston
Leonardo DiCaprio
Solange Knowles
Taylor Swift
Michelle Williams
Robert Pattinson
Blake Lively
Selena Gomez
Gigi Hadid
Benicio del Toro
Side by Side
False Lash Guide
Varied length spikes create texture and the illusion of depth without weighing down the lid.
Longer outer-corner lashes draw the eye outward and upward, counteracting the hood effect.
A uniform, moderate length that adds definition without overwhelming a hooded lid.
Applied only to the outer half, these open up the eye shape and are easier to manage on hooded lids.
A strong upward curl (D or L curl) lifts lashes away from the hood, keeping them visible throughout the day.
The guide also covers lash curlers, mascara recommendations, and step-by-step instructions for fixing false lashes on hooded eyelids.
Full Lash Guide →Get in Touch
Whether you are just beginning your makeup journey or have been experimenting with different looks for years, we are glad you are here.
General Feedback
Share your thoughts on the site or suggest topics you'd like covered.
Looking for a Specific Tip?
Ask about a particular technique or eye-shape challenge.
Product Questions
Questions about products mentioned across the site.
Human Resources or Business Inquiries
Partnership, collaboration, or business-related correspondence.